Categories
Consult-Liaison Nonfiction Public health psychiatry Seattle

Constraining Choice Sets.

The rains have finally returned to Seattle, though the wildfires continue to burn:

Wildfires from Google Maps as of the morning of 2022 Oct 24.

That map does not include the entirety of Washington State (there are more fires outside the boundaries of that image), or the fires burning in neighboring Idaho and Oregon.

While we did not experience the blood red skies that San Francisco experienced from the wildfires of the summer of 2020, the air was looked and smelled thick. Each whiff contained fragrant notes of Douglas Fir and perhaps Western Red Cedar, all overwhelmed by charred carbon. Landmarks disappeared into a gritty haze of grey. The evenings featured a crimson sun sinking into ashy layers of peach, pink, and coral.

By October 19th, Seattle had the worst air quality on the planet:
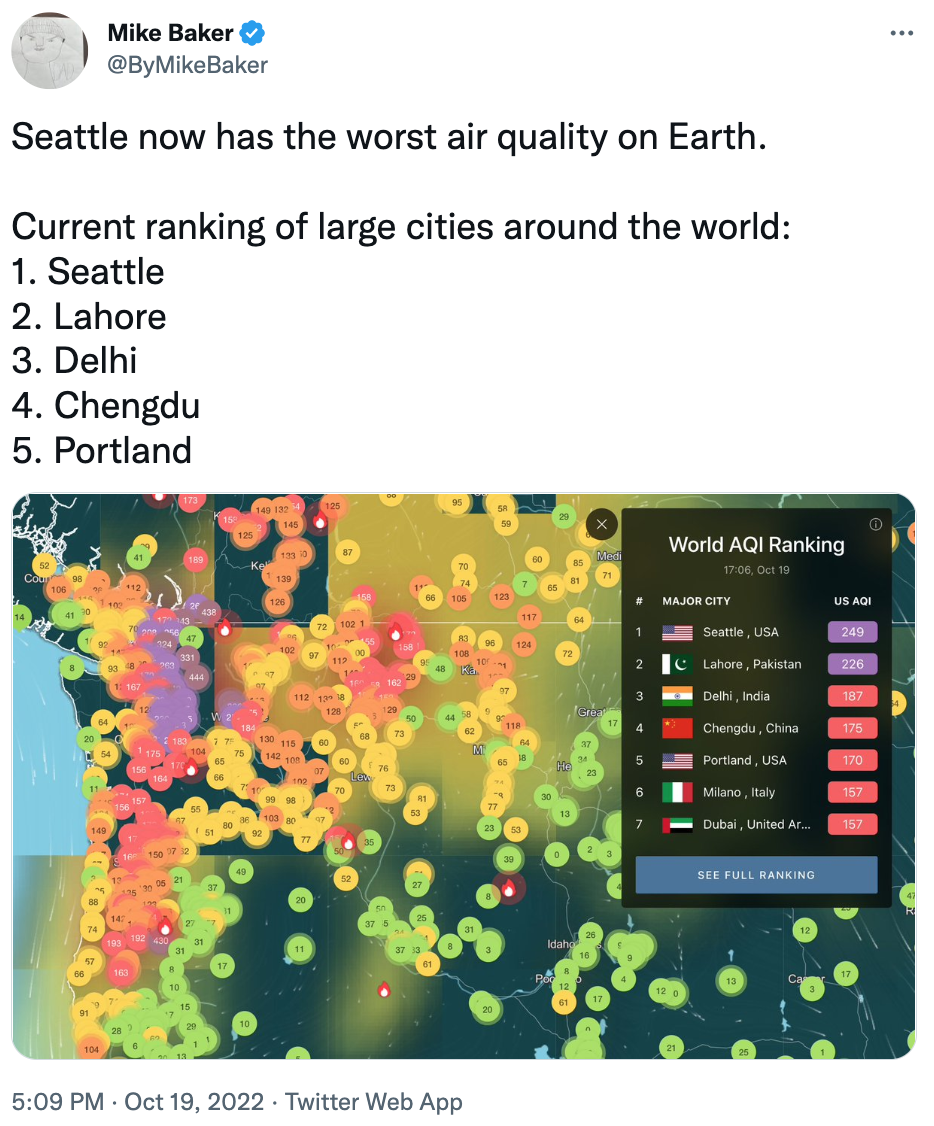
Conditions did not improve the next day. The Space Needle has a webcam (more precisely a “panocam”, as it provides a 360-degree view). Go take a look at it now; this is the grey pall that we embrace for much of the year. Despite this pewter drape, one can still see the surrounding buildings, lakes, and trees. Compare this to the view on October 20th:

(“Is the Mountain Out?” refers to glorious Mt. Rainier, the 14,410-foot tall stratovolcano that looms over the region.)

The rain finally arrived on October 21 and displaced the smoke:

Unfortunately, it did not extinguish the wildfires. Our neighbors to the east have yet to escape the smoke.

In addition to headaches, congestion, and watery eyes, people also experience psychological effects due to wildfires. I came across this paper in Nature Human Behavior from July 2022 that reports on one aspect of this: Exposures and behavioural responses to wildfire smoke (no paywall as of this writing). While the paper doesn’t quite answer the question I want to answer, it did report:

… during large wildfire smoke events, individuals in wealthy locations increasingly search for information about air quality and health protection, stay at home more and are unhappier. Residents of lower-income neighbourhoods exhibit similar patterns in searches for air quality information but not for health protection, spend less time at home and have more muted sentiment responses.

(For those who consider how your digital data gets used, the data for this paper came from Twitter, Google searches, and a real-time air quality monitor called PurpleAir, along with geographic income data.)

As we also have seen during the pandemic, people with lower incomes have less choices, even if they have access to similar information (emphasis mine):

Why do wealthier locations respond differently to smoke exposure? The measured differences do not appear to reflect differences in exposure information or in overall internet activity, given the consistent response of air-quality-related searches across income groups. Rather, the responses are consistent with lower incomes constraining choice sets and behaviours, including less flexibility in working from home, fewer resources with which to consider purchasing protective technology and (regarding the sentiment results) having other more pressing matters to worry about.

The Seattle Times published an article on October 20th that highlighted “constraining choice sets”. The King County Regional Homelessness Authority opened a “smoke shelter“, though few people used it. Why?

“The long-term effects of breathing in smoke is not going to be like the most highest of priority,” said an outreach worker. This is consistent with the findings from the article: While people living outside may have access to the internet, they likely are not seeking air quality monitors or information about filtration, as they do not have their own windows to close or own spaces to filter.

One of the conclusions of the article about wildfires could very well be applied to the pandemic: a “policy approach of promoting private provision of protection could be biased against disadvantaged groups”. I also suspect that the unhappiness the wealthier respondents reported as a result of wildfire smoke is not dissimilar from the ongoing unhappiness we all are seeing as a result of the pandemic and its social consequences. (It is likely that people who are poor are also experiencing unhappiness; they simply may not have the time, energy, or resources to feel it.)

Categories
Blogosphere Policy Public health psychiatry Systems

Prevention and Early Intervention in Psychiatry.

Two shops on a street, one a cafe and the other selling vintage goods. The building is made of brick and it's sunny outside.
Photo by Suzy Hazelwood

The inimitable Dr. Ryan McCormick recently wrote a piece that summarized research findings that he, as a primary care physician, can apply in clinical practice. In the section describing outcomes related to antidepressant dose, he notes:

As an aside, it may be shocking to note that psychiatrists prescribe only 21% of the antidepressants in the U.S., with the other 79% of prescriptions usually coming from primary care providers!

(Similarly, primary care providers write about half the prescriptions for benzodiazepines.)

Much of the burden of psychiatric services falls to primary care and emergency medicine. Some data suggest that nearly 60% of US counties do not have a single psychiatrist. While primary care and emergency medicine physicians can and do provide psychiatric services, they can be put into positions where they are addressing psychological issues beyond their scope of expertise. I mean no disrespect in writing that. Just as it is a terrible idea for me, a psychiatrist, to manage complex diabetes, it is unideal for non-psychiatrists to manage complex psychiatric conditions.

Sometimes people end up developing complex psychiatric symptoms and conditions because they are unable to access support, care, and services earlier. As a result, larger numbers of people end up accessing services in urgent or emergent ways (e.g., emergency departments and criminal-legal systems). Local jurisdictions then receive increasing demands to build crisis response systems. For example, Seattle-King County recently announced a future ballot measure to build five mental health crisis centers in the region.

There will always be a role for crisis centers, as life is unpredictable and collisions of fate and bad luck can result in crises. However, if the crisis system has the most open doors and is the most robust part of the system, then this will only increase the number of people who will use that system.

We can pick any point in a theoretical journey through the crisis system, but let’s start with the crisis center. Let’s say that all five centers have been established and that these centers receive the most dedicated funding and attention. Maybe John Doe is able to access the crisis center directly, which is a boon to first responders and emergency departments—it’s one less person they need to provide care for (and they’re often are not the best suited to give support, anyway). Once John Doe is not as overwhelmed, what are the next steps?

If the crisis centers have received the most dedicated funding and resources (staffing, advertising, etc.), that probably means that other resources—like step-down units or outpatient clinics—will not have the same level of support. Thus, it might be weeks or maybe even a few months before John can get into a clinic.

John can do the best that he can to make it until that appointment, but what if something else happens and he need urgent care? His choices might be limited to an emergency department (which, no offense to my ED colleagues, are not therapeutic places to be) or to return to a crisis center. He might call a first responder, but that might entail an encounter with law enforcement (which is often not people’s first preference). Unless other resources are made available—unless there are other pathways he can take—he will continue riding the merry-go-round that is the crisis response system.

This is why it is essential to build and sustain prevention and early intervention system while also building crisis response structures. The tired phrase is “moving upstream”, but that is the most stable way to get people out of the crisis system.

I agree (to a point) with the New York Times’s editorial board: The Solution to America’s Mental Health Crisis Already Exists. This article provides an accurate history of how a vision of community-based care for some of the most psychiatrically ill and vulnerable people in our communities got degraded. Do I think it is the solution? Only when I feel particularly optimistic. Do I think it is a solution that could yield great rewards? Yes, though ideally this would be paired with other non-medical, community-driven prevention and early intervention efforts.

Prevention and early intervention systems don’t need to formally reside with medical or legal structures. In fact, it is better for the whole community if they don’t. (Let’s not kid ourselves: The vast majority of people don’t want to spend time in the health care system, particularly with psychiatrists. The health care system can do amazing things, but it is also rigid, expensive, and requires people to jump through a lot of hoops.)

Nathan Allebach recently created a TikTok video that describes the decline of “third places” (and I am relieved that he recognizes that car-dependent suburban sprawl isn’t the sole cause community erosion). I’m not saying that community erosion is the primary cause of psychiatric symptoms and distress. However, the presence of social bonds and community could not only alleviate symptoms, but could also prevent some psychological problems. What if interpersonal social networks were robust and included both more and different kinds of people and perspectives? What if fewer people felt lonely and “Good Neighbor Day” didn’t have to be a thing? (Full disclosure: I have a professional crush on Dr. Vivek Murthy.)

If it is true that at least some psychiatric conditions are “medicalized” sociological problems, then this is an arena where non-medical (though not necessarily political!) interventions could be invaluable. Fewer people would believe that their only option is to ask Dr. McCormick for antidepressant medication for anxiety and depression. Non-medical, community-based activities might be sufficient. Fewer people would need to go to emergency departments or crisis centers because resources and options in the community would be inviting and easily accessible. Maybe two crisis centers, instead of five, would suffice. And people would spend less time with (and money on) health care professionals and services, and more with people they want to spend time with… people in their chosen communities.

Categories
Policy Public health psychiatry Reading Systems

Is Mental Health Political?

Items neatly arranged on a desk, including a clipboard with a blank white sheet of paper and a magnet board with separate letters spelling "politics".
Photo by Tara Winstead

Here’s another piece in the New York Times’s series on mental health and society: Mental Health is Political. (Forgive the generous quoting and quotation marks that follow.) Dr. Carr says:

In medicine, examples of reification [the process by which the effects of a political arrangement of power and resources start to seem like objective, inevitable facts about the world] are so abundant that sociologists have a special term for it: “medicalization,” or the process by which something gets framed as primarily a medical problem. Medicalization shifts the terms in which we try to figure out what caused a problem, and what can be done to fix it. Often, it puts the focus on the individual as a biological body, at the expense of factoring in systemic and infrastructural conditions.

She goes on to say:

When it comes to mental health, the best treatment for the biological conditions underlying many symptoms might be ensuring that more people can live less stressful lives.

… after clarifying that she is

not arguing that mental illnesses are fake, or somehow nonbiological. Pointing out the medicalization of social and political problems does not mean denying that such problems produce real biological conditions; it means asking serious questions about what is causing those conditions.

The crux of her argument is this (emphasis mine):

This principle is what some health researchers mean by the idea that there are social determinants of health — that effective long-term solutions for many medicalized problems require nonmedical — this is to say, political — means.

I think I understand what she is arguing here: There are systems in our culture that contribute to mental distress and illnesses. I generally agree with this. If entry level jobs consistently paid wages that allowed people to rent apartments in cities where they work, that would reduce psychological pressure. The stress of long commutes, public transportation, and car and gasoline costs would disappear. People would have more time to enjoy healthful activities instead of commuting. If people are spending more on housing than they can afford, this leads to the tension of living paycheck to paycheck. Insecurities related to eviction and homelessness grow. None of this contributes to psychological wellness.

However, I also wonder how she defines “political” throughout this piece. Is all psychological distress really “political” in nature? For people who experience auditory hallucinations and delusions, is their psychological distress “political”? (Recall that there are people with a diagnosis of schizophrenia who are not indigent: They sustain employment, pay their rent on time, and lavish their pets with treats.)

Are all nonmedical interventions for mental illnesses—whether “medicalized” or not—“political” interventions? At various times and places, there has been alignment between the political beliefs of the community and those in political power. Did rates of mental distress and illnesses significantly decline? (I don’t know the answer to this; if you do, let me know.) If alcohol use disorders are mental illnesses, does this mean that Alcoholics Anonymous and other 12-step groups are “political” interventions? If people who have lost loved ones to suicide and convene as a group to express grief and support, is this a “political” act?

Should we still describe our psychological distress as “political” when life is inherently stressful? Is the act of commiserating with other medical professionals for support during the pandemic a political act? Maybe it is; maybe we must turn to each other because we recognize that health authorities apparently cannot and will not provide more support to us. But maybe it’s not; maybe this is a community of care we intentionally cultivated over time.

I found some validation for my reactions in this Gawker piece: Failure to Cope “Under Capitalism”. Clare Coffey describes

an application of “the personal is political” so expanded in scope that, for a certain kind of person, personal problems, anxieties, and dissatisfactions are illegible or illegitimate unless described as political problems.

She further notes that

[the] invocation [of capitalism] immediately establishes a phenomenon in the realm of the political, without any further work required.

… if only political problems are legitimate, only political solutions are admissible. This has the odd effect of filtering all attempts at self-integration through a political lens.

By describing problems (like capitalism) and solutions as political, perhaps this absolves us of the work we can (and sometimes need) to do. How can one person’s action have any meaningful impact on a political problem like capitalism? Aren’t systems, by definition, much larger than individual people? She then points out:

But in fact there is no one to adjudicate between you and capital, no one to say yes, that really is too much, let’s reassign this project. …

There is no political program that will release you from the necessity of doing more than you should have to or feel capable of doing, in politics as in every other part of life.

I appreciate her exhortation:

This is your life. You do not have time to wait for the revolution to begin living it. You will always be able to find someone to give you permission not to live it. But no one is coming along to live it for you.

To be clear, I am not at all suggesting that we can eradicate mental distress and illnesses by simply yanking on those bootstraps. The statement that “mental health is political”—to me, at least—removes any agency we have as individuals. Yes, political interventions and actions can improve population (mental) health. However, some political interventions will have little to no impact on individual psychological health. There are choices we all can make, on our own, that can help improve our own psychological wellbeing. Furthermore, we each can make choices everyday that can improve the psychological health of the people within our six-foot radius. Our actions don’t have to be political statements.

Given the work that I do, I don’t need much persuasion to believe that systems have many direct and indirect adverse effects on people’s health. It also seems unreasonable, though, that politics will always provide solutions for mental distress and illness.

Categories
COVID-19 Nonfiction Public health psychiatry

16 People.

Content warning: This post discusses death and suicide.

Photo by George Becker

Early in my training, someone older and wiser than me made a comment in passing:

There are two types of psychiatrists: Those who have had patients die by suicide, and those who have not.

I assume (perhaps incorrectly) that all psychiatrists eventually join the group where someone under their care dies by suicide. These deaths change us.

The first time I learned that someone under my care died from suicide was during my intern year. I didn’t know him well; I do not remember his name. I was working in a psychiatric unit in a hospital and had worked with him for only one or two days. He had a diagnosis of a psychotic disorder. My sole memory of him is his flat, unblinking expression while he looked at me. Though his face showed little emotion and he said few words, he radiated discomfort.

Within a week of his discharge from the hospital, he had jumped off of a bridge.

I didn’t know how to react. I don’t remember if we had a conversation about him, if anything else had happened, or what we could have done differently.


I do remember the name of the person who killed himself after he and I had been working with each for nearly a year. He was the first of “my” patients who died by suicide.

He earned a professional degree long ago, but was living in a shelter. Alcohol brought him comfort, though it drowned his career. He argued a lot. This was the primary way he knew how to interact with people. Despite his pugnacious manner, he and I built and maintained a respectful rapport.

The medical examiner ruled that he had died from an overdose, though the official did not deem this a suicide. The toxicology report stated that there was methadone and alcohol in his system. He did not like and never used opiates.

I still think of him a few times a year. I still wish he had talked to me before he ended his life.


In any given year, I learn that one or two people under my care have died. Most of the time, the cause isn’t suicide. People age; people get sick; bad luck strikes.

Between January of 2020 and June 2022, sixteen (16) people under my care died. None of them died from Covid. The youngest was in their late 20s; the oldest was in their mid-60s. A few died from suicide; others died from medical problems (some acute, some not). Many died from overdoses. Maybe they were intentional; maybe they weren’t. I will never know.


I recently spoke with a former colleague about the various losses we have experienced over the pandemic.

“No one wants to hear it,” she said with some bitterness. “People are tired of hearing sad or bad news, so they don’t ask about our work or how we’re doing.”

She’s not wrong. It’s not easy for me to talk about it, either, as talking about it means I have to think about it, and it’s hard to think about things that do not make sense and may never make sense: What happened? What happened to us?

Maybe I just want people to know that actual human beings died, that I knew these people, that all these people meant something to someone, that they meant something to all of us who had the opportunity to know them. I wish I could tell you more about the guy who made a handmade Christmas card for me, even though he had yelled at me the first time we met just six months prior. I wish I could tell you more about the woman who had several weeks of sobriety before she collapsed on the sidewalk, her heart pulseless. I wish I could tell you more about the man who always called me “Ms. Dr. Maria” and offered me home-cooked food whenever I visited him at his apartment.

That’s only three people. There are 13 others.


If you’ve lost someone during the pandemic, you are far from alone. A poll from 2021 (!) revealed that about 1 in 5 Americans are close with someone who has died of COVID-19. (Recall that over one million people in the US have died from Covid.) Suicide remains a leading cause of death in the US, with certain groups at higher risk than others. (Also remember that we all can help prevent suicides; it doesn’t have to be the only option.)

It’s okay to feel sad, angry, or disappointed; you feel how you feel. Things will change, as they always do, though they may not change as fast as we want them to. It’s also scary to express vulnerability. Voluntarily shedding the crusty carapace to reveal the soft tissue within, however, may be the best (or only) path forward.

Categories
Medicine Policy Public health psychiatry

Recent Readings.

(Note: There are two purposes to this post: One, to get back into a routine of writing and posting. Two, I moved my website to a different host (those of you viewing the actual website will see that the design is different). Because it will never be perfect (because what is?), I am posting as a public test to fix what needs to be fixed.)

Here are some interesting articles I’ve read recently, some of which are prompts for future posts here:

NPR: Stressed out about climate change? 4 ways to tackle both the feelings and the issues. I am largely unfamiliar with the literature on psychiatric conditions and climate change, though have read a paper or two (not recently) about the association of increased violence among people with increases in temperatures. I must also confess that that my current faith in psychiatry to address this in a practical way is brittle: Organized psychiatry (in the United States, at least) seemed unenthusiastic about supporting population mental health during the pandemic. Despite the urgent mental health consequences of Covid-19, organized psychiatry in the US seemed instead enamored with the topic in the next bullet point.

Wired: Is the Psychedelic Therapy Bubble About to Burst? A new paper argues that excitement has veered into misinformation—and scientists should be the ones to set things straight. I find myself feeling annoyed with the mushrooming ecstasy related to psilocybin and LSD (see what I did there?), among others. There are a number of reasons for this; I will be the first to state that some of my reasons are not valid. Much of my irritation stems from the limited evidence (at this time) to support psychedelics for more severe conditions, the limited number of people who can actually access this intervention (who can afford this? who has eight hours to spend with two therapists?), and why We as a Society do not instead invest in population-level interventions so fewer people will develop trauma-, depression-, and anxiety-related conditions (e.g., ensuring children aren’t hungry; supporting literacy and education so people have skills for employment; etc.).

The Hill: Suffering from burnout, doctors are working drunk or high on the job: report. A new report found the health care industry has been too slow to address its mental health crisis among doctors and nurses and often treats mental health as secondary to physical health. “Over the last three months, 1 in 7 physicians admitted to consuming alcohol or controlled substances at work.” This data came from interviews from a mental health company, so there’s potentially a lot of bias in the results. I am sorry to say, though, that I wasn’t surprised to learn this. Some health care workers were drinking or using controlled substances at work before the pandemic.

n+1: Lab-Leak Theory and the “Asiatic” Form. What is missing is a motive. I did not find this to be an easy read, though it engaged me enough that I was able to get through it. In short, the author, Andrew Liu, argues that the appeal of Covid-19 coming from a lab leak is a reflection of historical (and ongoing?) exoticization of the Orient, as well as fears of China’s economic power.

New York Times: Yes, We Mean Literally Abolish the Police. and Truthout: I Stole to Feed My Family and Was Incarcerated. We Need Resources, Not Prisons. I am not an abolitionist, though there are days when I wish I could be successfully persuaded to become one. (This reflects what appears to be my declining idealism as I age.) To be clear, I do not think incarceration has been or is an effective solution for many (and maybe most?) behaviors and problems. This conclusion comes from my experience working in a jail and with people who are poor and marginalized. However, examples easily come to mind for how law enforcement and incarceration have had some value: Consider Jeffrey Epstein or Ted Bundy. I don’t know what the answer is, though I do not think either pole (e.g., police state or abolition) are useful or desired solutions. I am open to changing my mind. (Related: This Twitter thread on the role of child protective services.)

New Yorker: The Lottery. Shirley Jackson wrote this short story in 1948 and I only learned of it in 2022! If you’ve never heard of it before, please go read it: It has excellent structure, which helps drive the story to its haunting and disturbing conclusion.